




What do you do when there are no drugs to treat a crippling disease, especially one that is so rare that there are only approximately one in two million patients worldwide?
You simply have to deal with it the best way you can and hope that someday, there will be drugs to help.
That is the predicament of patients with fibrodysplasia ossificans progressiva (FOP) or “Stone Man Syndrome”, a rare musculoskeletal condition where, after birth and progressively through life, muscles and tendons gradually transform into bone (a process called ossification).
This creates a second “skeleton” of extra bone, which makes movement impossible.
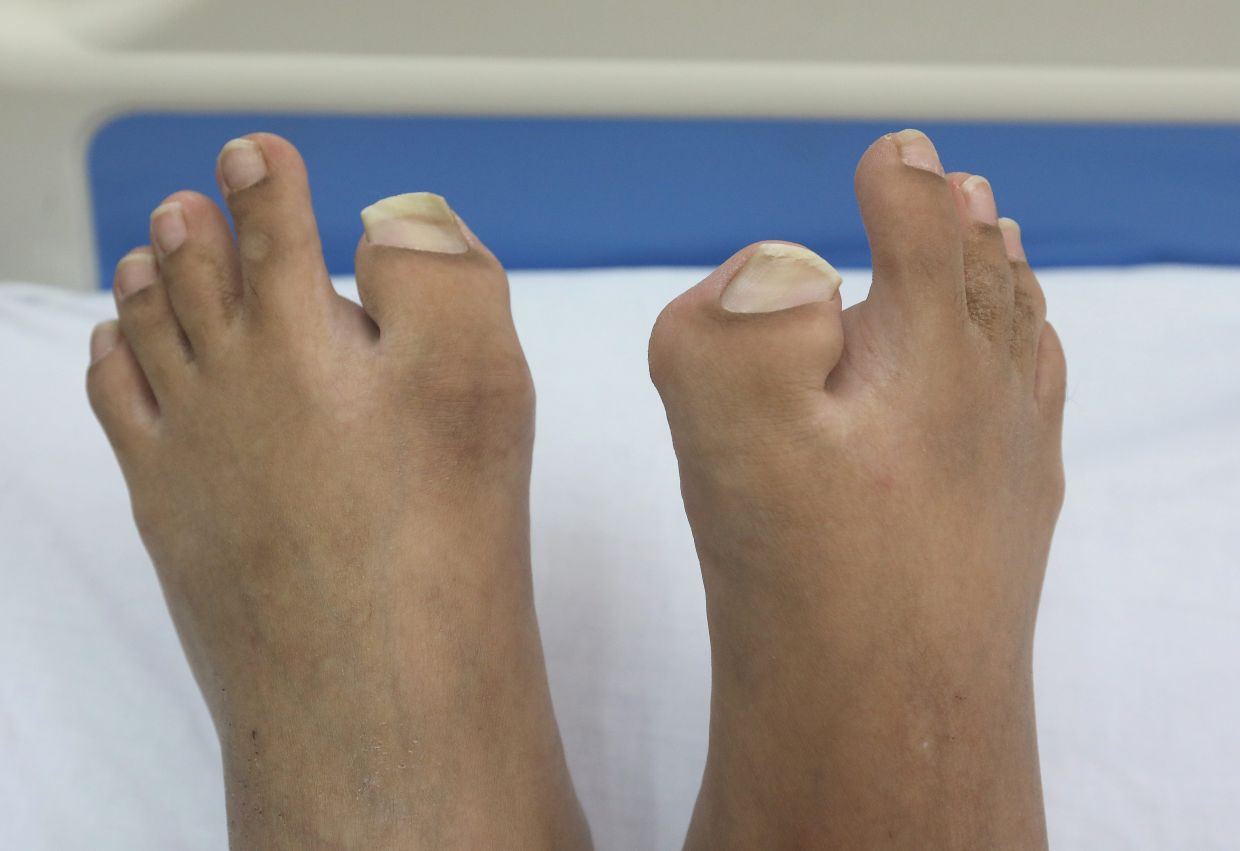
There is no ethnic, racial, gender or geographic predilection for FOP and children who have the condition appear normal at birth except for congenital malformations of the big toe.
Globally, it is estimated that there are 800 FOP patients, with nine cases genetically diagnosed in Malaysia.
“When there is no treatment, they don’t get a genetic diagnosis, only a clinical diagnosis, with most presenting at the orthopaedic clinic because of extra bone manifestation.
“Bone is supposed to be formed within skeletal tissues, but in FOP, because the gene is not working properly, trauma and inflammation results in new bone formation outside skeletal tissues,” explains Hospital Kuala Lumpur (HKL) consultant clinical geneticist Dr Kavitha Rethanavelu.
An overactive receptor
FOP is caused by a mutation of the ACVR1 gene, which is autosomal dominant.
This means that just one copy of the altered gene inherited from a parent is sufficient to cause the disorder.
The mutation can also occur spontaneously.
In fact, most cases of FOP result from new mutations in the gene that occur in people with no history of the disorder in their family.
This gene provides instructions for making a member of a protein family called bone morphogenetic protein (BMP) type I receptors.
This ACVR1 protein is found in many tissues of the body, including skeletal muscle and cartilage.
It helps control the growth and development of bones and muscles, including the gradual replacement of cartilage by bone that occurs in normal skeletal maturation from birth to young adulthood.
Studies show that mutations in the ACVR1 gene disrupt mechanisms that control the receptor’s activity.
As a result, the receptor is turned on when it normally should not be, leading to too much activity, causing overgrowth of bone and cartilage.
Dr Kavitha says: “When the muscles, ligaments and tendons lose elasticity, the region becomes painful and swollen, and with ossification, patients lose mobility as they are unable to straighten their joints.
“They become progressively disabled and since the diaphragm is also a skeletal muscle, they develop an extra bone formation around the rib cage, restricting their lung expansion.
“When they are bedbound, they tend to develop breathing issues and get an infection, and that causes early death by 20 to 30 years.”
As their physical disability is quite significant, their ability to reproduce is also affected.
However, FOP patients have normal cognitive function, as the disease doesn’t affect their intellectual capability.
No treatment available
The peak time that FOP shows itself is between the ages of eight and 12, when the child is active and falls, and complains of painful joints.
In the past, doctors made a diagnosis based on clinical evaluation or tissue biopsies, but the latter actually injures the body further and doesn’t confirm the disease.
“Now, diagnosis is better as access to genetic testing is better and less expensive.
“In the Internet era, patient knowledge is also better,” adds Dr Kavitha.
The earliest known case of FOP was that of Harry Raymond Eastlack Jr who was born in 1933 in Philadelphia, Pennsylvania, United States.
Except for malformed big toes, he exhibited no other symptoms until he broke his left femur in 1938.
Instead of the bone fusing together, a noticeable bulge formed on the front of his left thigh and he was subsequently diagnosed with FOP.
By 1946, his body was permanently locked in an angled position, his spine was fused, and the muscles in his upper back were ossified.
Eastlack was eventually bedridden and died of pneumonia six days short of turning 40.
In developed countries, patients live to their 50s as they get optimal care, so death is postponed by a few years.
As of now, there is no treat- ment for FOP, although several clinical trials testing potential drugs are ongoing.
“Treatment is only supportive as injections cause more damage.
“We tell patients to move less, try non-pharmacological methods such as meditation or clinical hypnosis.
“Since they are in constant pain, we prescribe non-steroidal anti- inflammatory drugs (NSAIDs), muscle relaxants, opioids, etc.
“For some reason, the heart is the last to be affected, but we don’t have enough data to conclude why,” Dr Kavitha explains.
A glimmer of hope
In rare diseases, clinical trials on children are difficult as parents are often wary of trying unproven treatments on their offspring.
So the trials have to be conducted on adults first before children can be roped in.
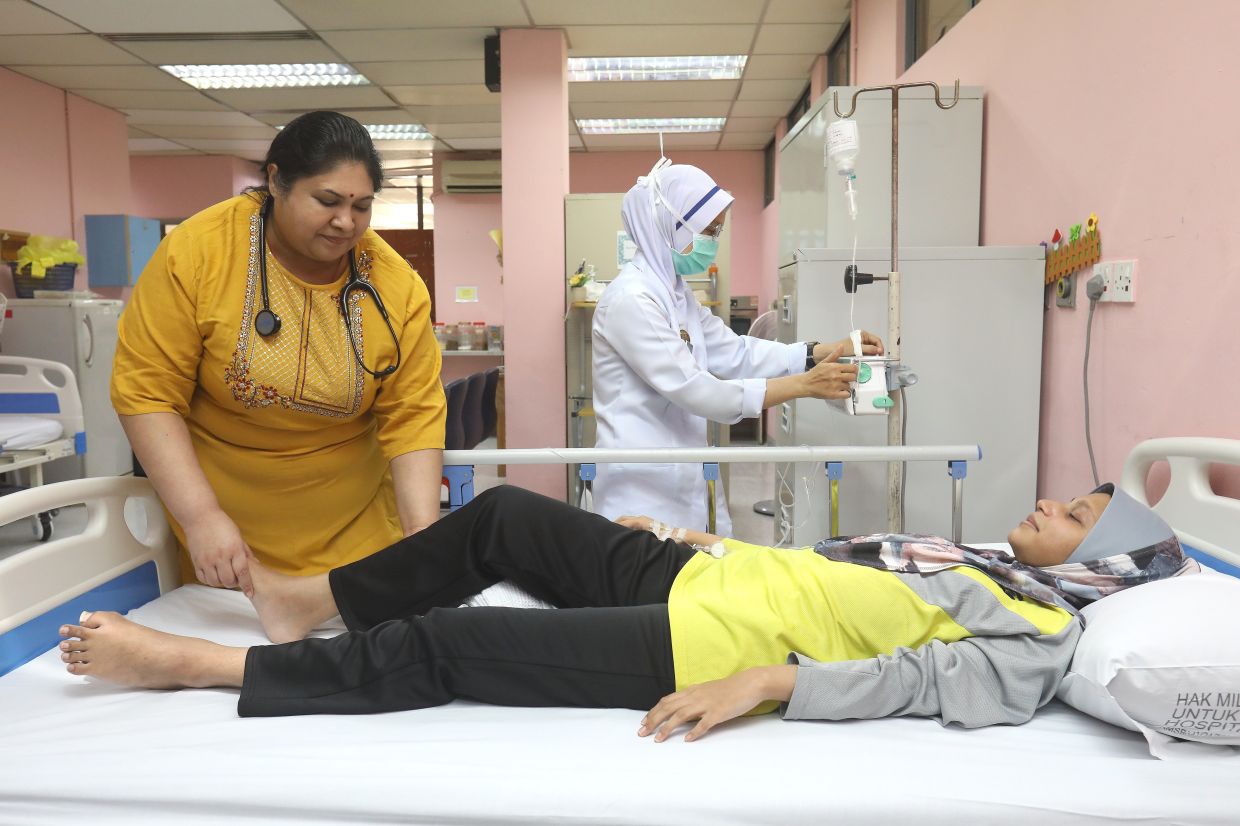
Four Malaysian FOP patients are currently involved in an international phase 3 clinical trial using the drug garetosmab.
The participants either receive a placebo, or a low dose or a high dose of the drug, and as a double-blind trial, neither doctor nor patient knows what they are receiving.
Garetosmab, a fully human monoclonal antibody, recently received Orphan Drug status for FOP from the US Food and Drug Administration (FDA).
An orphan drug is a drug for a rare disease or condition.
Some rare disease treatments have been “orphaned” or discontinued because there was not enough financial incentive to continue development or production.
ALSO READ: Special exceptions for orphan medicines to treat rare diseases
The trial is designed to evaluate the safety of garetosmab, and whether monthly dosing will reduce the formation of new ossification and reduce the signs and symptoms of flare-ups.
Malaysia’s participation happened by chance, but Dr Kavitha, who is the principal investigator here, is thrilled.
She shares: “One of our patients’ mother (Qureshiah Abdul Basher) is an active member of the International FOP Association and they contacted us (HKL) to ask if we were interested in the clinical trial.
“At that time, the daughter was only 17, so I wrote to the researchers to appeal if they could wait until she turned 18 to participate as they were closing the trial enrolment.
“They agreed and she was the last patient to be enrolled in June last year (2024).”
ALSO READ: Hope arises for these rare disease patients who have 'stone man syndrome'
FOP patients, three of whom StarHealth interviewed, are required to make 17 visits to HKL to receive their monthly infusion.
Once the trial is over in July (2025), all the participants will get the drug for free according to the dosage required, until the results are published and garetosmab is available in the market.
However, one Malaysian participant has already pulled out due to logistical and health reasons.
ALSO READ: ‘I’m like a mannequin,’ says this rare disease patient
“These drugs are expensive and if we discontinue treatment, the symptoms might return, so the pharmaceutical company has verbally promised to continue providing the drug for a while,” says Dr Kavitha.
Already, some participants are noticing positive changes and hope for better days ahead.
Already a subscriber? Log in
Get 20% OFF The Star Digital Access
Cancel anytime. Ad-free. Unlimited access with perks.


